Sunday, August 26, 2012

FDA: J&J Unit (Synthes) Recalls Potentially Flammable Bone Putty


The health regulator said certain lots of bone putty made by Johnson &Johnson unit Synthes were recalled as there was potential for the putty to catch fire if it came in contact with electrosurgical cautery systems during surgery.

The Hemostatic Bone Putty is used to stop bone bleeding by creating a physical barrier along the edges of bones damaged by trauma or cut during a surgical procedure.
The recall, which has been classified as Class I, or the most serious type of recall, was initiated on July 5.
Synthes had issued a medical device recall letter on July 5 requesting medical facilities to examine their inventory and immediately stop using the identified part and lot numbers of the putty manufactured between July 6, 2011 and December 14, 2011.
Synthes has been in the news for all the wrong reasons, Symthes is unusual in that it is one of a few cases in which company execs have been sentenced to a term of imprisonment for a misdemeanor violation of the Food, Drug and Cosmetic Act. The individual defendants, by virtue of their jobs, were “responsible corporate officers” at various time during the circumstances surrounding the clinical trial that was described in the indictment.


And what exactly took place? From May 2002 until fall 2004, a Synthes subsidiary called Norian, as well as Synthes and the former execs, ran unauthorized trials of their Norian XR and Norian SRS devices, which were bone cements used in surgeries to treat vertebral compression fractures of the spine, or VCR, a painful condition commonly suffered by the elderly, according to the feds.


The surgeries were performed despite a warning on the FDA labeling for Norian XR that cautioned against this use, and in the face of serious medical concerns about the safety of the devices when used in the spine, according to the feds. But they apparently disregarded the warnings. For instance, the feds say that, before the marketing program began, pilot studies showed the bone cement reacted chemically with human blood in a test tube to cause blood clots. The research conducted in a pig also showed that such cement-caused clots became lodged in the lungs.


Just the same, the Synthes gang marketed the device for VCFs without conducting testing that needed FDA approval, the marketing did not stop until after a third patient had died on the operating table.The trials were conducted at various US hospitals and selected surgeons were approached during so-called ‘Test Market Kick-Off’ meetings and a forum in 2003 and early 2004, according to the feds, who say about 52 spine surgeons were trained.


What’s more, after the death of that third patient in January 2004, they did not recall Norian XR from the market – which would have required them to disclose details of the three deaths to the FDA, according to the feds. Instead, they “compounded their crimes by carrying out a coverup in which they made false statements to the FDA during an official inspection in May and June 2004.” However since the purchase by J&J, it is J&J who now hold the legal burden.

To date:
2011 - Three executives from Synthes, a device maker that was recently purchased by Johnson & Johnson, were sentenced to prison for their roles in an unapproved trial of a bone-cement drug that led to three patient deaths. All four plead guilty to one misdemeanor count of shipping an adulterated and misbranded product in interstate commerce.Thomas Higgins, 55, a former president of the Synthes spine division, and Michael Huggins, 54, a former president of Synthes North America, were each sentenced to nine months. John Walsh, 48, who was director of regulatory and clinical affairs, was sentenced to five months. Richard Bohner, 57, sentenced at a later date to 8 months. Each must also pay a $100,000 fine. 
Feb, 2012 - FDA Warning Letter 
Latest 2012 - FDA: J&J Unit Recalls Potentially Flammable Bone Putty


Wednesday, August 22, 2012

Symphogen Publishes Final Rozrolimupab (SYM001) Phase 2 Trial Results in ITP in BLOOD Journal


 — The hematology journal BLOOD published today a full-length article describing final Phase 2 data for Symphogen’s rozrolimupab, a novel human recombinant mixture of 25 antibodies which all are manufactured simultaneously from a single batch. The data demonstrates rozrolimupab’s favorable safety profile and its induction of a rapid increase in platelet counts in patients with Primary Immune Thrombocytopenia Purpura (ITP). Professor Tadeusz Robak, MD, University of Lodz, Poland, is the first author of the article entitled “Rozrolimupab, A Mixture of 25 Recombinant Human Monoclonal RhD Antibodies, in the treatment of Primary Immune Thrombocytopenia” which has been prepublished in First Edition of Blood and can be viewed on Blood Online at http://bloodjournal.hematologylibrary.org/content/early/recent.
The Phase 2 study was an open-label, multi-center clinical trial evaluating the efficacy, safety, and tolerability of rozrolimupab (SYM001) in adult, RhD positive, non-splenectomized ITP patients. A total of 61 patients were treated with single doses from 75µg/kg to 300µg/kg as single i.v. infusions of 15-20 minutes’ duration. The trial demonstrated that at 300µg/kg, 8 of 13 (62%) of patients responded at day 7. Already within 5 to 8 hours after rozrolimupab administration, 23% of the patients achieved platelet responses (≥ 30×109/L and increase in platelet count by > 20×109/L from baseline). Median time to response was 59 hours (approximately 2.5 days) and the median duration of response was 14 days.
The most common adverse events observed, were headache (20%), mostly mild or moderate, pyrexia (13%), chills (10%), and fatigue (8%). Four serious adverse events considered related to study drug were reported: decreased hemoglobin, extravascular hemolysis/dizziness and two cases of transient rise in D-dimer values without clinical symptoms.
According to Professor Robak, “These Phase 2 results suggest an efficacy and safety profile similar to that seen with plasma derived immunoglobulin products. It seems promising that rozrolimupab rapidly yields platelet responses. This unique recombinant human monoclonal antibody mixture, rozrolimupab can be produced indefinitely and may represent a novel and convenient replacement for blood-derived immunoglobulins with more limited supply.”
Kirsten Drejer, Symphogen chief executive officer, added, “Symphogen has reached an important milestone by generating clinical proof of concept for a product consisting of a mixture of 25 monoclonal antibodies. The multicenter study included involvement of the regulatory authorities of the USA, Europe and Asia, and we are confident that antibody mixtures represent a viable new class of antibody therapeutics offering well-characterized and potentially more efficacious alternatives to existing treatments.”

Wednesday, August 15, 2012

New Study Reveals Wide Variation In Blood Transfusion Practices During Surgery


 According to a new study in the July 2012 print edition of Anesthesiology, blood transfusion, the most common procedure performed in U.S. hospitals1, has wide variation in frequency by surgical procedure and physician as well as wide variation in the hemoglobin trigger used to help decide whether to transfuse.2 The study also showed a significant number of transfusion decisions are made without laboratory hemoglobin measurements. The research adds to the growing clinical evidence highlighting the need for improved blood-management strategies. It also underscores the opportunity for noninvasive and continuous total hemoglobin (SpHb®) monitoring from Masimo (NASDAQ:MASI) to facilitate optimal transfusion decision making to improve patient safety and reduce costs.
In the study, conducted at Johns Hopkins Hospital in Baltimore, Maryland, researchers collected data on 48,086 surgical patients over 18 months and evaluated blood transfusion frequency and hemoglobin triggers by surgical procedure and physician. A total of 2,981 patients (6.2%) received an intra-operative red blood cell transfusion, with two-thirds of those patients receiving two or more units. Transfusion rates varied up to threefold between different physicians performing the same procedure (p<0.05). The average transfusion hemoglobin trigger used to determine need for blood transfusion varied widely with both surgeons (7.2 g/dL to 9.8 g/dL, p=0.001 and anesthesiologists (7.2 g/dL to 9.6 g/dL, p=0.001). The ending hemoglobin values after the last recorded transfusion also varied widely for both surgeons (8.8 g/dL to 11.8 g/dL, p=0.001) and anesthesiologists (9.0 g/dL to 11.7 g/dL, p=0.0004). A recent laboratory hemoglobin measurement was not available when 31% of transfusion decisions were made.
Blood transfusions carry risks. In a previous meta-analysis of 45 studies evaluating the risks of blood transfusion, 42 studies showed a significant link to mortality, infection, or adult respiratory distress syndrome.3 In contrast to the historical belief that withholding transfusions harms patients, multiple randomized controlled trials have now proven that restrictive transfusion practice is safe.4,5,6 This has led recent transfusion guidelines to focus transfusion decisions on the overall patient condition and to suggest hemoglobin transfusion triggers of 6-7 g/dL for most patients and above 7 g/dL only in select, high-risk patients.7,8,9
Blood transfusions are also one of the largest cost centers in hospitals. While the material cost of blood ranges from $200 to $300 per unit, the additional costs from storage, labor, and waste result in an actual cost per unit between $522 and $1,183.10 In addition to the cost of blood itself, each unit of blood transfused increases the cost of care, with even higher costs incurred when patients are transfused at higher hemoglobin levels.11
A recent systematic evaluation of 494 studies concluded that 59% of transfusions were “inappropriate” based on their impact on patient outcomes.12 The risks and costs of blood transfusion paired with unnecessary transfusions led the Joint Commission in 2011 to introduce new patient blood management measures that hospitals are being encouraged to adopt as a quality indicator.13 The new measures include recording the clinical indication for transfusion along with the hemoglobin value of the patient prior to each unit transfused. With the need to stem rising health care expenditures, the Joint Commission and the American Medical Association have targeted blood transfusion procedures as one of the top procedures to reduce in a “National Summit on Overuse” scheduled for September 2012.14
There is no doubt that clinicians desire the best care for their patients without unnecessary costs, but they are also limited in their precise ability to determine need for transfusion with existing tools. Estimates of blood loss in the operating room can be inaccurate. Researchers at Duke University recently reported estimated surgical blood loss exceeded measured blood loss by more than 40% (860mL vs. 611 mL, p< 0.0001).15 The likely reason for this discrepancy is the inability to accurately estimate blood loss based on visual inspection of blood and fluid in suction canisters and surgical sponges. While estimating blood loss is challenging and laboratory hemoglobin results are only availably intermittently and are often delayed, transfusion decisions are made in real time. Acknowledging these challenges, the Duke Researchers stated: “Use of bedside hemoglobin concentration devices and continuous, noninvasive hemoglobin monitors may improve transfusion decisions.”
Masimo’s breakthrough SpHb measurement allows clinicians to noninvasively and continuously monitor hemoglobin. Results of an earlier randomized controlled trial conducted by researchers at Massachusetts General Hospital and Harvard Medical School showed that SpHb helped anesthesiologists reduce the frequency of blood transfusion by 87% (from 4.5% to 0.6%, p=0.03) and quantity of blood by 90% (from 0.1 to 0.01 units per patient, p<0 .0001=".0001" 327="327" in="in" orthopedic="orthopedic" patients="patients" sup="sup" surgery.="surgery." undergoing="undergoing">16
Dr. Aryeh Shander, Executive Medical Director at the Institute for Patient Blood Management & Bloodless Medicine Surgery and Chief of Anesthesiology and Critical Care Medicine at Englewood Hospital & Medical Center in New Jersey, stated: “The ability of Masimo’s noninvasive hemoglobin technology to continuously monitor hemoglobin during surgeries can offer earlier, real-time information that can result in diagnosis leading to interventions other than transfusion. And fewer unnecessary transfusions can mean improved patient outcomes.”
This year Masimo launched the Blood Transfusion Related Cost Reduction guarantee program (BTR-CR, “Better Care”) to help hospitals improve patient care and reduce costs. BTR-CR guarantees that a hospital’s blood transfusion-related cost reductions will be greater than the cost of SpHb monitoring. 

1 AHRQ, Center for Delivery, Organization, and Markets, Healthcare Cost and Utilization Project, Nationwide Inpatient Sample, 1997 and 2007.
2 Steven M. Frank, M.D., Will J. Savage, M.D., Jim A. Rothschild, M.D., Richard J. Rivers, M.D., Paul M. Ness, M.D., Sharon L. Paul, B.S., M.S., John  A. Ulatowski, M.D., Ph.D., M.B.A. “Variability in Blood and Blood Component Utilization as Assessed by an Aesthesia Information Management System.” Anesthesiology, July 2012 – Volume 117 – Issue 1 – p 99–106 doi: 10.1097/ALN.0b013e318255e550
3 Marik, P. E. and H. L. Corwin (2008). “Efficacy of red blood cell transfusion in the critically ill: a systematic review of the literature.” Crit Care Med 36(9): 2667-74.
4 Carson, J. L., M. L. Terrin, et al. (2011). “Liberal or restrictive transfusion in high-risk patients after hip surgery.” N Engl J Med 365(26): 2453-62.
5 Hebert, P. C., G. Wells, et al. (1999). “A multicenter, randomized, controlled clinical trial of transfusion requirements in critical care. Transfusion Requirements in Critical Care Investigators, Canadian Critical Care Trials Group.” N Engl J Med 340(6): 409-17.
6 Hajjar, L. A., J.-L. Vincent, et al. (2010). “Transfusion Requirements After Cardiac Surgery: The TRACS Randomized Controlled Trial.” JAMA 304(14): 1559-1567.
7 American Society of Anesthesiologists Task Force on Perioperative Blood Transfusion and Adjuvant Therapies: Practice Guidelines for Perioperative Blood Transfusion and Adjuvant Therapies: An updated report by the American Society of Anesthesiologists Task Force on Perioperative Blood Transfusion and Adjuvant Therapies. Anesthesiology 2006; 105:198 –208
8 Napolitano LM, Kurek S, Luchette FA, Corwin HL, Barie PS, Tisherman SA, Hebert PC, Anderson GL, Bard MR, Bromberg W, Chiu WC, Cipolle MD, Clancy KD, Diebel L, Hoff WS, Hughes KM, Munshi I, Nayduch D, Sandhu R, Yelon JA, American College of Critical Care Medicine of the Society of Critical Care Medicine, Eastern Association for the Surgery of Trauma Practice Management Workgroup: Clinical practice guideline: Red blood cell transfusion in adult trauma and critical care. Crit Care Med 2009; 37:3124 –57
9 Society of Thoracic Surgeons Blood Conservation Guideline Task Force, Ferraris VA, Brown JR, Despotis GJ, Hammon JW, Reece TB, Saha SP, Song HK, Clough ER, Society of Cardiovascular Anesthesiologists Special Task Force on Blood Transfusion, Shore-Lesserson LJ, Goodnough LT, Mazer CD, Shander A, Stafford-Smith M, Waters J, International Consortium for Evidence Based Perfusion, Baker RA, Dickinson TA, FitzGerald DJ, Likosky DS, Shann KG: 2011 update to the Society of Thoracic Surgeons and the Society of Cardiovascular Anesthesiologists blood conservation clinical practice guidelines. Ann Thorac Surg 2011; 91:944 – 82
10 Shander, A.,A. Hofmann, et al. “Activity-based costs of blood transfusions in surgical patients at four hospitals.” Transfusion 50(4): 753-65.
11 Murphy, G. J., B. C. Reeves, et al. (2007). “Increased mortality, postoperative morbidity, and cost after red blood cell transfusion in patients having cardiac surgery.” Circulation 116(22): 2544-52.
12 Shander, A., A. Fink, et al. (2011). “Appropriateness of allogeneic red blood cell transfusion: the international consensus conference on transfusion outcomes.”Transfus Med Rev 25(3): 232-246 e53.
13 Gammon HM, Waters JH, Watt A, Loeb JM, Donini-Lenhoff A: Developing performance measures for patient blood management.  Transfusion 2011; 51:2500 –9.
14 Joint Commission Perspectives.  The Joint Commission Continues to Study Overuse Issues.  Volume 32, Number 5, 2012 : 4-8(5).
15 Hill, S., Broomer, B Stover, J,  White, W. (2011). Accuracy of estimated blood loss in spine surgery. American Society of Anesthesiologists Annual Conference, San Diego, CA
16 Ehrenfeld JM, Henneman JP, Sandberg WS. “Impact of Continuous and Noninvasive Hemoglobin Monitoring on Intraoperative Blood Transfusions.” American Society Anesthesiologists. 2010;LB05

Tuesday, August 7, 2012

Cohera Medical Completes Enrollment of U.S. Clinical Trial of TissuGlu® Surgical Adhesive


PITTSBURGH, Aug. 7, 2012 /PRNewswire/ -- Cohera Medical, Inc.®, a leading innovator and developer of absorbable surgical adhesives and sealants, today announced the completion of enrollment of its prospective, multicenter, randomized clinical trial for its lead product, TissuGlu® Surgical Adhesive inthe United States.

The study is evaluating the effectiveness of TissuGlu on the reduction of wound drainage and post-surgical complications in abdominoplasty surgeries. The study included 150 patients enrolled at five sites throughout the U.S., including Atlanta, Baltimore, Charlotte, St. Louis, and Washington DC.

"We are delighted to complete enrollment in this critical trial for TissuGlu, which has the potential to eliminate wound drainage issues from large flap procedures," said Dr. Joseph Hunstad of the Hunstad-Kortesis Center for Plastic Surgery, Charlotte, NC. "The trial results so far are very promising for both the surgeons and the patients."

Completion of enrollment of the study marks a significant milestone in Cohera Medical's progression of its lead product toward commercialization in the United States. The Company will use the results from the study to submit a PMA application for TissuGlu with the FDA. There are currently no medical devices approved by the FDA, or in pivotal clinical trials, for a synthetic adhesive indicated for approximation of tissues in large flap surgeries.

"We are extremely pleased to have reached this very significant milestone in our clinical study," saidPatrick Daly, President and Chief Executive Officer of Cohera Medical. "It is a testament to the surgeons and the Cohera team to enroll 150 patients in 90 days. We are encouraged by the positive feedback from the TissuGlu investigators and look forward to our work with the FDA to make TissuGlu available to surgeons and patients throughout the U.S."

Cohera Medical received CE Marking approval for TissuGlu and began selling product to hospitals and surgeons in Germany in September 2011. To date, TissuGlu has been used successfully in over 500 surgical procedures in Germany by leading plastic and reconstructive surgeons.

Currently, most patients who undergo abdominoplasty procedures and other large flap procedures require the insertion of drains to remove fluids that accumulate under the skin at the surgical site. In some cases, drainage is inadequate and the excess fluid accumulation (seroma) requires additional procedures for removal. TissuGlu adheres the tissue flap created during the procedure to the underlying tissue, helping to reduce the fluid that can accumulate in the space and ultimately reducing the time to drain removal. The use of TissuGlu may shorten the length of time that drains need to be in place, leading to a more comfortable recovery and a quicker return to normal activity for patients.

Thursday, July 19, 2012

Sysmex and Siemens Renew Global Partnership for Hemostasis Solutions and Services


President and CEO: Hisashi Ietsugu) and Siemens Healthcare Diagnostics (HQ: NY, USA; CEO: Michael Reitermann) have announced the signing of a five-year global supply, distributorship, sales and service contract extension under which clinical laboratory customers around the world can retain access to the largest portfolio of innovative hemostasis instruments and reagents through 2018. The companies, which began partnering in 1995, also agreed to continue joint product development activities, ensuring customer access to new hemostasis technology. The signing occurred during the 2012 AACC and ASCLS Annual Meetings and Clinical Lab Expo in Los Angeles, California.
The large assortment of hemostasis products covered in this latest agreement is used by clinical laboratories to test for blood disorders in patients and to monitor patients on blood-thinning medication. To date, Sysmex and Siemens have released to market a variety of advanced solutions, including the recently launched Sysmex CS-5100*(1), the top-end model in Sysmex's CS hemostasis analyzer series, the Sysmex® CA-600 Systems*(1), a new line of compact, fully automated hemostasis analyzers, as well as several new Siemens INNOVANCE™ reagents.
"We are pleased to extend our longstanding relationship with Siemens Healthcare Diagnostics," said Hisashi Ietsugu, President and CEO of Sysmex Corporation. "Our partnership in the field of hemostasis combines the strength of two leading diagnostics companies whose joint expertise offers best-in-class solutions to the laboratory. We remain committed to further expand our offerings with enhanced clinical utility and workflow efficiency."
"Our shared goal to deliver high quality products and services that address our customers' needs is a key reason for the success of our 17-year relationship," said Michael Reitermann, CEO, Siemens Healthcare Diagnostics. "Sysmex and Siemens remains a reliable partnership for customers worldwide amidst an evolving hemostasis market. Together, we will continue offering customers the broad portfolio of hemostasis solutions they have come to expect from us and we will also focus on delivering next-generation technologies going forward."

Sunday, July 15, 2012

It's Perclot AMP.......No, It's Endoclot AMP

Cryolife last month announced that finally they had some good news regarding the litigation with Medafor, and under terms of the settlement, Medafor has agreed to pay CryoLife $3.5 million in cash. However the Atlanta based CryoLife foray into the powdered Hemostat market segment may still prove "interesting". When making their arrangement with Chinese Starch Medical for rights to Perclot in all territories worldwide excluding China, Hong Kong, Macau, Taiwan, North Korea, Iran and Syria. They also included the following in the contract:


  1.5 Product Applicators, Etc. SMI agrees to promptly notify CryoLife of all improvements to applicators, tips and other accessories included within or used in connection with the Products, including all new applicators, tips and other accessories. All such improvements and any such new applicators, tips or accessories to the Products shall be included within the Products and the Parties shall adjust the catalog of Products to reflect these new products, with any transfer price to be negotiated in good faith, but based solely on costs to SMI for such improvements and/or new applicators, tips and accessories. The Parties agree that the Endoscopic applicator system used for powder delivery via gastrointestinal endoscope, as further described on Schedule 2.1 is not an improvement or new applicator and is not included in this Agreement.

2.   Distribution

    2.1  Limitations on SMI Activities. During the term of this Agreement SMI agrees (i) to sell the Products exclusively to CryoLife for use in Permitted Clinical Applications within the Territory, (ii) to refrain from selling or licensing any Products to any Existing Distributor or Third Party for sale or distribution in Permitted Clinical Applications within the Territory, (iii) to refrain from directly or indirectly marketing, promoting, or encouraging any Third Party to market, promote or Distribute the Products for any of the Permitted Clinical Applications within the Territory, (iv) to refrain from licensing or transferring any AMP™ Technology to any Third Party within the Territory for the purpose of manufacturing any Products upon terms or conditions that would enable or allow such Third Party to sell any Products for Permitted Clinical Applications within the Territory. In addition, SMI agrees that it shall refrain until January 1, 2015 from (A) directly, or indirectly selling, permitting to sell, market, promote or encouraging third parties to sell, permit to sell, market or promote any Competitive Product (defined below) for any Permitted Clinical Application within the Territory or (B) licensing or transferring to any Third Party technology that would enable or allow any Third Party to manufacture any Competitive Product within the Territory. The provisions of the foregoing sentence shall be deemed further modified so that SMI may only take the actions described therein if SMI complies with Section 1.4 (and therefore CryoLife does not match the right of first refusal set forth therein). As used herein, “Competitive Product” means any powdered absorbable surgical hemostat that is intended for or could be used for a Permitted Clinical Application. The foregoing limitations do not apply to sales by SMI of those products described on Schedule 2.1.

Read the full document HERE

.
Now Cryolife and their partners face the interesting prospect of Chinese made Perclot AMP particles meeting them in the EU re-branded as "Endoclot".  

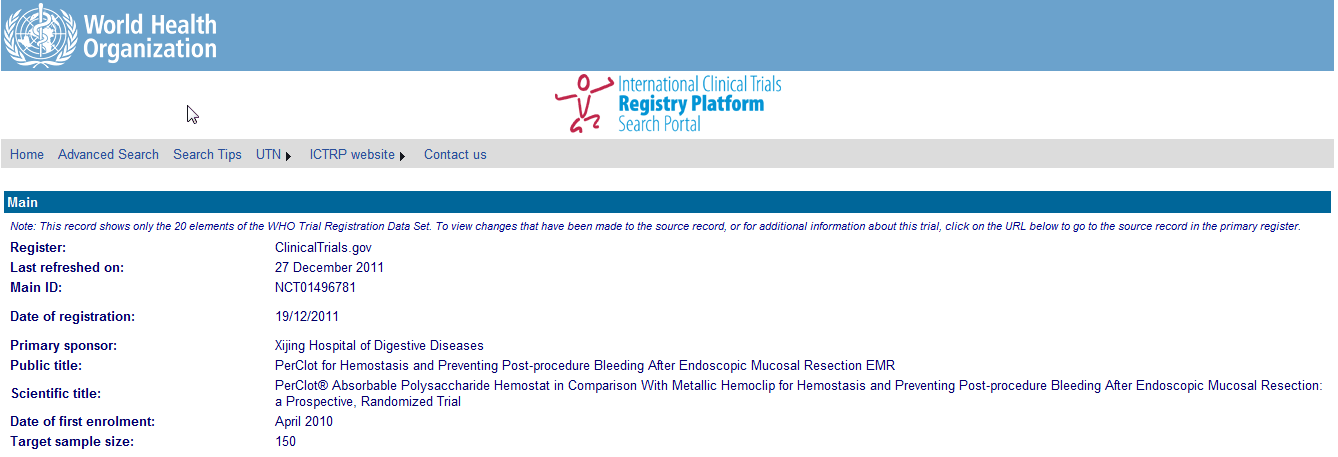
As can be seen HERE the original Chinese Xijing Hospital trial changes for the use of AMP show the changes from perclot to "endoclot", but the endoclot webpage discusses AMP particles....see HERE. 

The CRY Q2 Earnings Conference Call is scheduled for 7/31/2012. 
Click the images below to enlarge


Thursday, July 12, 2012

Study to Investigate the Safety and Effectiveness of TissuGlu in Abdominoplasty Surgeries Without the Use of Postoperative Drains


Cohera Medical, Inc.®, a leading innovator and developer of absorbable surgical adhesives and sealants, today announced the start of a no-drain clinical trial in 30 patients at two prominent surgery centers in Germany.  The study will investigate the safety and effectiveness of TissuGlu® Surgical Adhesive in the reduction of wound drainage, post operative seroma and related complications in abdominoplasty patients without the use of drains.
Currently, most patients who undergo abdominoplasty procedures and other large flap procedures require the insertion of drains to remove fluids that accumulate under the skin at the surgical site. In some cases, drainage is inadequate and the excess fluid accumulation (seroma) requires additional procedures for removal. The drains are often painful for the patient, can lead to infection and can impact the recovery process.
TissuGlu adheres the tissue flap created during the surgical procedure to the underlying tissue, helping to reduce the space where fluids can accumulate thereby eliminating the need to use surgical drains.  The ability to perform the procedure without drains would lead to a more comfortable recovery and a quicker return to normal activity for patients.
"We are excited to be part of this study utilizing TissuGlu to eliminate postoperative drains," said Dirk Richter, MD, of Wesseling, Germany.  "We look forward to enrolling more patients and believe that conducting abdominoplasty procedures without the need for drains would represent a significant improvement in patient care and comfort in these procedures.  The initial patients enrolled appear to be doing very well, with no seromas or complications reported in the first 48 hours after surgery."
"Initiation of this 'no drain' trial represents a major goal for TissuGlu," said Patrick Daly, President and Chief Executive Officer of Cohera Medical.  "We continue to make positive patient outcomes a priority and believe the elimination of post-surgical drains is an important milestone."
Drain management and discomfort is the leading patient complaint for plastic surgery procedures according to the top plastic surgery publications.  In addition, complication rates from seroma formation range from 15% to 52% following abdominoplasty procedures.


Monday, July 9, 2012

China Biologic Receives SFDA Manufacturing Approval Certificate for Human Coagulation Factor VIII

China Biologic Products, Inc., a leading fully integrated plasma-based biopharmaceutical company in China, today announced that its indirectly owned subsidiary, Shandong Taibang Biological Products Co., Ltd. ("Taibang") has received a manufacturing approval certificate from the China State Food and Drug Administration ("SFDA") for Human Coagulation Factor VIII ("FVIII"). With this certificate, the only approval remaining for Taibang's commercial production of FVIII is the SFDA's good manufacturing practice ("GMP") certification of the FVIII production line itself.

Taibang began research for FVIII in 2007 and successfully developed the technology in 2008. The Company conducted clinical trials from 2009 to 2010. In June 2010, the Company submitted required materials to Center for Drug Evaluation for approval to start manufacturing and passed on-site products verification in January 2011. The Company received official manufacturing approval certificate on June 21, 2012. FVIII will be primarily used in the treatment of hemophilia A.

Mr. David Gao, Chairman & CEO, said, "Receiving SFDA manufacturing approval represents the culmination of more than five years of work and the first technological approval of a coagulation factor product developed by Taibang. With the addition of Factor VIII, we should soon be able to offer three major categories of blood products: albumin products, immunoglobulin products and coagulation factor products. This will further strengthen our competitive position as a leading plasma-based biopharmaceutical company in China."

"We are very proud to bring FVIII to hemophilia A patients in China," continued Mr. Gao. "We believe that Human Coagulation Factor VIII addresses a critically unmet need of a large patient population and helps ease under-supply of coagulation products. Although it is not possible to specify a definitive timeframe in which we will receive GMP approval, we expect our FVIII production to be inspected by SFDA and then GMP certified by the end of 2012. Going forward, we intend to continue to develop and manufacture life-enhancing, effective, quality-assured products."

About China Biologic Products, Inc.

China Biologic Products, Inc., is a leading fully integrated plasma-based biopharmaceutical company in China. The Company's products are used as critical therapies during medical emergencies and for the prevention and treatment of life-threatening diseases and immune-deficiency related diseases. China Biologic is headquartered in Beijing and manufactures over 20 plasma-based products through its indirect majority-owned subsidiaries, Shandong Taibang Biological Products Co., Ltd. and Guiyang Dalin Biologic Technologies Co., Ltd. The Company also has an equity investment in Xi'an Huitian Blood Products Co., Ltd. The Company sells its products to hospitals and other healthcare facilities in China. For additional information, please see the Company's website www.chinabiologic.com .

Friday, June 8, 2012

Study with Fibrocaps(TM) Lead product on track for market launch in 2014


LEIDEN, The Netherlands & SEATTLE, Jun 06, 2012 (BUSINESS WIRE) -- ProFibrix B.V., a leader in the development of innovative bioactive products to stop bleeding (hemostasis), today announced the start of its pivotal Phase III clinical trial with Fibrocaps (FINISH-3) in spine, liver, vascular and soft tissue surgery.
FINISH-3 is a multicenter, randomized, single-blind, controlled Phase III trial of Fibrocaps in 672 surgical patients with mild to moderate surgical bleeding. The main objectives of the study are to demonstrate superior efficacy of Fibrocaps vs. gelatin sponge within each surgical indication, and to confirm the overall safety results from the Phase II Fibrocaps trials completed in 2011.
Dr. Paul Frohna, Chief Medical Officer of ProFibrix said: "We are very pleased to announce the randomization and treatment of the first patients in the international FINISH-3 trial less than 4 months after completing our End-of-Phase II meeting with the U.S. FDA. Based on the excellent Phase II study results, the investigators are very eager to enroll their patients into our study and we remain on track for regulatory filings in the U.S. and EU in 2013. Based on the product's unique properties, and the overwhelmingly positive feedback we are receiving from the surgical community, we believe Fibrocaps should be able to capture a substantial share of the US$ 1 billion topical hemostat market."
The Fibrocaps used in the pivotal Phase III clinical trial has been manufactured by ProFibrix's commercial manufacturing partner Nova Laboratories Limited (Leicester, UK). Peter White, Managing Director of Nova Laboratories said: "It is great to be part of this exciting project and to manufacture the Phase III product and I am looking forward to our long term collaboration."
About Fibrocaps
Fibrocaps is a mixture of two essential blood clotting proteins, fibrinogen and thrombin, and is a unique dry powder topical fibrin sealant being developed to stop bleeding during or after surgery. Fibrocaps is clearly differentiated from existing liquid tissue sealants and hemostats: it is ready for immediate use, and is stable at room temperature.
About the FINISH-3 trial
FINISH-3 is a prospective, randomized (2:1), single-blind, controlled, pivotal Phase III trial of Fibrocaps vs. active control in 672 subjects undergoing spinal (n=168), liver (n=168), vascular (n=168) and soft tissue surgery (n=168). The study will be conducted at 65 sites across Europe and the U.S. Estimated completion date is May 2013.
For more details on the study, please go to http://www.clinicaltrials.gov .
About ProFibrix
ProFibrix ( www.profibrix.com ) was founded in 2004 and is headquartered in Leiden, The Netherlands, with a subsidiary in Seattle, WA, USA. The company leverages its expertise in fibrinogen technology to develop and bring to market innovative products for the hemostasis and regenerative medicine markets. Human fibrinogen plays a pivotal role in blood clotting and tissue healing. ProFibrix is led by a team with extensive commercial, clinical and scientific experience in the hemostasis field.
SOURCE: ProFibrix

Thursday, June 7, 2012

HemCon Adds Barry Starkman as CEO


HemCon Medical Technologies, Inc., an industry leader in hemorrhage control technologies and developer of lyophilized (freeze-dried) human plasma for the U.S. Army, announced today the appointment of Barry Starkman as Chief Executive Officer. Starkman joins HemCon with more than 30 years of experience in biologics and medical technology manufacturing.
"As we reorganize and restructure with the objective of successfully exiting Chapter 11, Barry is an extremely important addition to the HemCon team. His leadership and expertise will prove valuable in realizing the full potential of our lyophilized plasma program (LyP program), and in developing the optimal strategy for the Medical Device division," said Bill Wiesmann, Chairman and Co-Founder of HemCon. "Barry rounds out our executive team, working with Nick Hart who will continue his role as President and CFO."
As Chief Executive Officer, Starkman's focus will be on the execution and delivery of the LyP program through Phase 2 clinical trials and planning and executing on facility expansion to allow HemCon to enter Phase 3 clinical trials for the LyP program. He will also review the Medical Device division fully to determine the optimal means by which this business can be developed and contribute towards HemCon's overall financial performance.
Starkman's experience spans pharmaceutical products, biotech, and medical devices, matching the commercial applications for HemCon's LyP Program and Medical Devices division. His background also includes manufacturing management in the areas of facilities design, cGMP manufacturing requirements and Lean 6 Sigma applications.
Prior to joining HemCon, Starkman served as Vice President of Operations at Promega, where he was responsible for global manufacturing, planning and logistics for the $300 million organization. Starkman had previously overseen the design, construction, start-up and operation of Genentech's $450 million state-of-the-art formulation, packaging and distribution facility in Portland, serving as General Manager. Earlier in his career, Starkman worked for 24 years for Merck taking on increasing responsibility which culminated at Director of Manufacturing within Vaccine Operations.
"I am thrilled to become part of the HemCon team and bring my leadership skills to a company with breakthrough innovation in the plasma world and a proven track record of efficacious and safe medical devices which give HemCon immense potential," said Barry Starkman. "I look forward to working with the team in a timely exit from Chapter 11 and then helping HemCon realize its potential as a highly successful and viable enterprise."
HemCon Medical Technologies, Inc. ( www.hemcon.com ), founded in 2001, develops, manufactures, and markets innovative technologies for rapid delivery of plasma and hemostatic devices for the control of bleeding resulting from trauma or surgery. HemCon products are designed for use by military and civilian first responders as well as medical professionals in hospital and clinical settings where rapid supply of plasma and control of bleeding are of critical importance. HemCon is headquartered in Portland, Ore., with additional commercial operations in Ireland and the Czech Republic.
SOURCE: HemCon Medical Technologies, Inc.